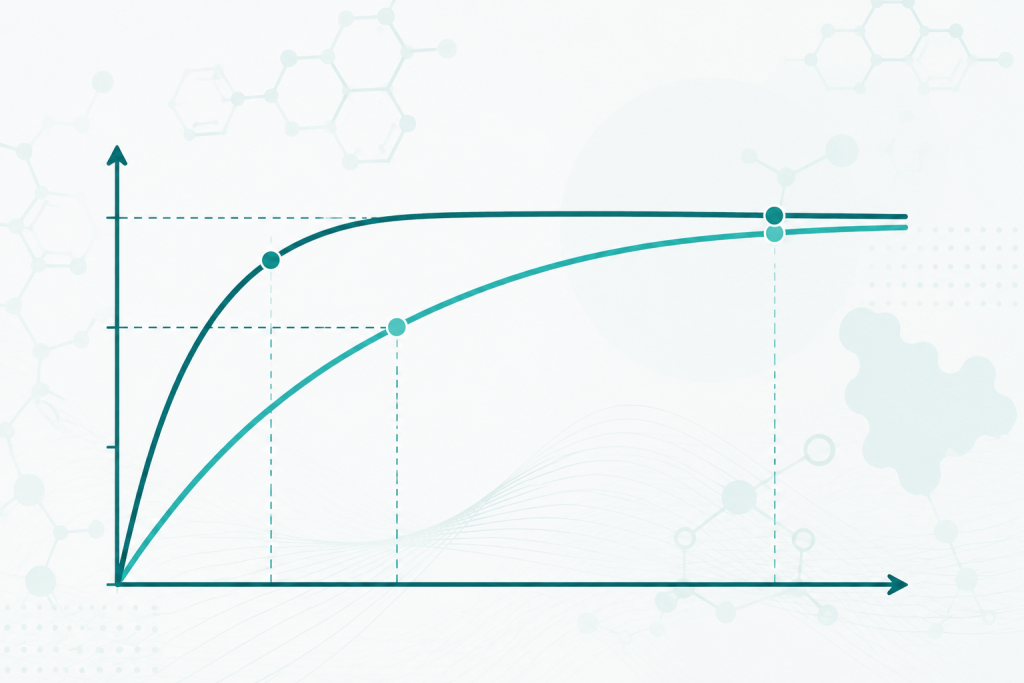
When someone starts a steroid cycle with a long-ester compound, the first few weeks can feel like a slow climb. Strength and appearance changes often arrive gradually because blood hormone levels are still building up. Frontloading is the practice of taking a larger dose at the very beginning of a cycle so those levels rise towards the target range sooner. It sounds like a shortcut, but it is really just an application of pharmacokinetic principles to the way esters release hormones over time.
- Frontloading means using a higher opening dose so blood levels approach the target range faster than with equal doses from day one.
- It works because long esters accumulate slowly; without a loading dose, several weeks can pass before concentrations level off.
- It is not a universal shortcut. Ester length, injection frequency, and total weekly exposure still set the real timeline, and side-effect risk can rise with a larger initial dose.
What Is Frontloading in Steroid Cycling?
Definition: loading dose technique to reach peak blood levels faster
Frontloading is a dosing strategy in which the first one or two administrations of an injectable compound are larger than the maintenance dose used later in the cycle. The goal is to fill the body’s “drug reservoir” more quickly so the active substance reaches a concentration that would normally take weeks to achieve through equal repeated doses.
In practical terms, if a user plans to run 500 milligrams of testosterone enanthate per week, a frontloaded start might involve a larger first injection or a higher first-week total. After that, dosing returns to the planned maintenance amount. The aim is to shift more of the planned exposure to the start of the cycle, although a higher opening dose can increase the total amount used over a fixed cycle unless later doses are adjusted.
Medical origin (loading doses in pharmacology for IV, IM, oral drugs)
The concept of a loading dose is not unique to bodybuilding. It is a standard idea in clinical pharmacology. Doctors sometimes give a larger first dose of a medication so that therapeutic blood levels are reached quickly, followed by smaller maintenance doses to keep those levels stable.
Examples include certain IV antibiotics, where clinicians want high tissue concentrations quickly, and some oral drugs with long half-lives, where waiting for steady state through repeated small doses would delay the effect. The same logic applies to intramuscular injections: a larger initial load can push concentrations up faster than a series of identical injections. Of course, the medical setting involves careful monitoring, precise calculations, and patient-specific factors that do not directly transfer to unsupervised use.
Frontloading vs standard equal dosing throughout cycle
With a standard equal-dose protocol, every injection is the same size and spaced at the same interval. Blood levels rise gradually because each new dose adds to what is left from previous doses. After several half-lives, the amount entering the body roughly equals the amount leaving it, and blood concentrations stabilise around a steady state.
Frontloading interrupts that symmetry. The first dose is larger, so the starting concentration is higher. Maintenance doses then hold the level rather than continuing to build it. If the loading dose is calculated well, the peak-to-trough range can be similar to what equal dosing eventually produces, but the timeline to get there is compressed.
Why it takes weeks for steroid levels to ramp up without frontloading
The reason for the slow ramp-up is accumulation. After the first injection, the body begins clearing the drug according to its half-life. When the second dose arrives, some of the first dose is still present, so the total amount in circulation is higher than the second dose alone. This process repeats with each injection.
It takes about four to five half-lives for blood levels to get close to steady state with repeated equal doses. For a compound with a half-life of around seven to ten days, that can mean three to five weeks before concentrations flatten out. During that window, the user may be operating at a lower exposure than intended, which is what frontloading is intended to shorten.
How Frontloading Works: Half-Life and Pharmacokinetics
Role of ester half-life in reaching steady-state blood levels
The half-life of an ester is the central variable that determines how fast blood levels rise and fall. Short esters, such as acetate or propionate, clear quickly and reach steady state within days. Long esters, such as cypionate, enanthate, decanoate, or undecylenate, stay in the body much longer and take weeks to accumulate.
This long residence time is a double-edged sword. It means injections can be spaced further apart, but it also means the early phase of a cycle is dominated by low, rising levels. Frontloading addresses the second issue by introducing more drug early on to compensate for the slow release rate of the ester.
Typical blood level curve: weeks to peak with equal doses
Imagine a graph of blood concentration over time for a long-ester compound injected once per week at a fixed dose. The first injection produces a noticeable spike, then a gradual decline. The second injection adds another spike on top of the remaining drug from the first. Each week, the baseline is a little higher than the week before, and the peaks and troughs begin to cluster around an average value.
That average value is the steady state, and it is not reached instantly. The curve looks like a staircase that becomes progressively flatter. For testosterone enanthate or cypionate, some users report that the cycle “feels” different by week three or four compared with week one. That subjective change may coincide with the pharmacokinetic curve approaching its plateau, but it is not a direct measure of blood concentration.
Loading dose calculation principle (higher initial dose to saturate faster)
The basic principle behind a loading dose is simple: introduce enough extra drug at the start to make up for the amount that would have accumulated from previous doses if the cycle had already been running. In an idealised model, the loading amount depends on the maintenance dose, the half-life, and the injection frequency.
For common weekly protocols, one rough example is that the first injection may be about double the maintenance injection, or the first-week total may be roughly double the planned weekly total. After that, the user returns to the normal schedule. This is not a universal formula: more precise calculations use exponential decay formulas and account for the exact half-life and injection interval. Because these calculations can be tedious, some people use steroid calculators to model the expected blood-level curve before making any dosing decision.
Example: frontloading testosterone cypionate or EQ
Suppose a user plans to inject 250 milligrams of testosterone cypionate every three and a half days, for a weekly total of 500 milligrams. Without frontloading, blood levels rise over several weeks. With frontloading, the first injection might be 500 milligrams, followed by 250 milligrams every three and a half days thereafter. This increases exposure during the opening period unless subsequent doses are adjusted.
Another common example is boldenone undecylenate, often called EQ. Its ester is very long, so ramp-up can be slow even by long-ester standards. Some users frontload EQ with a substantially higher first-week dose to bring levels up within a shorter period. The exact amount depends on the planned weekly dose and the user’s tolerance for a larger initial injection volume.
Benefits and Practical Use of Frontloading
Faster access to target blood concentration
The main theoretical benefit of frontloading is speed. By starting closer to the target concentration, the user spends less time below the intended exposure. For performance-oriented goals tied to a fixed-length cycle, that can mean more weeks of the cycle are spent near the intended level.
This is not the same as making the drug “work instantly.” The ester still has to be cleaved, the hormone still has to be released, and tissue responses still take time. Frontloading only compresses the pharmacokinetic ramp-up phase, not the biological response phase.
Reduced ramp-up time in cycle
For users running shorter cycles, the ramp-up period can take up a significant portion of the total time. A twelve-week cycle with a long ester might only reach its plateau around week four or five without frontloading. Frontloading can shift that plateau earlier, leaving more of the cycle near the desired level.
Even on longer cycles, some people prefer the psychological clarity of knowing that levels are closer to their intended range from the start. Others would rather avoid a higher early dose and wait through a slower rise.
When frontloading is applied (first compound use, cycle start)
Frontloading is usually applied at the very beginning of a cycle, especially when the cycle is built around one or more long-ester compounds. It is also considered when a user is introducing a new compound for the first time and wants to evaluate how they respond at target levels without waiting through a long accumulation period.
It is less common with short-ester compounds because those already reach steady state quickly. It is also less common when a user is already on a steady maintenance dose and simply adding another compound, since the baseline hormone environment is already elevated.
User reports: does it make compounds work faster?
Anecdotal reports are mixed, with some users saying frontloading is noticeable, especially with long esters. They may say that the cycle “kicks in” sooner, that early strength changes arrive faster, or that the wait for visible effects feels shorter. Others report little difference and prefer the simplicity and smoother side-effect profile of equal dosing from the start.
These reports are difficult to evaluate because placebo effects, training conditions, nutrition, and sleep all influence how a cycle feels. Pharmacokinetic theory supports the idea that blood levels can reach a plateau sooner with a properly calculated frontload. Whether that translates into a meaningfully different outcome depends on the individual and the cycle structure.
Frontloading Protocols and Steroid Calculators
Dosing strategies: how much higher for the loading phase
There is no single frontloading formula that applies to every compound. A common example is to double the first injection or the first week’s total dose, then return to the maintenance plan. For example, a 600 milligram per week enanthate cycle might begin with 1,200 milligrams in the first week, split into two or more injections, followed by 600 milligrams per week. Unless later doses are adjusted, this raises the total amount used over a fixed cycle.
Some users prefer a more conservative approach, adding only 50 to 100 percent extra to the first injection rather than doubling. This may reduce the initial spike while still shortening the ramp-up. The appropriate approach depends on injection frequency, compound half-life, total weekly dose, and individual sensitivity to hormone fluctuations.
Using steroid calculators to plan frontload and backload
Steroid calculators are online tools that model blood concentration over time based on dose, half-life, and injection schedule. They are useful for visualising how a frontload changes the curve compared with equal dosing. By entering different opening doses, a user can see when the curve reaches the target range and how high the initial peak may be.
These calculators are educational tools, not medical devices. They rely on simplified pharmacokinetic models and may not account for individual differences in metabolism, injection depth, carrier oil, or ester hydrolysis rate. They can illustrate why frontloading shortens the ramp-up, but their outputs should not be treated as a substitute for clinical advice. For a breakdown of specific compounds and their half-lives, check the main reference.
Typical protocols for common esters (cypionate, enanthate, undecanoate)
Testosterone cypionate and enanthate are often discussed in relation to frontloading because their half-lives are long enough to make ramp-up noticeable, but short enough that a frontload may accelerate it. One example for either involves a first injection roughly twice the maintenance injection, followed by the regular schedule.
Testosterone undecanoate has an extremely long half-life, so frontloading is less common and less practical. Even with a larger opening dose, the compound releases slowly over many weeks. Anyone seeking a shorter ramp-up may consider that a different ester has different pharmacokinetic properties, rather than trying to force a quick release from undecanoate.
| Ester | Rough half-life | Common frontload approach |
|---|---|---|
| Testosterone propionate | Short (days) | Rarely frontloaded; reaches steady state quickly |
| Testosterone enanthate | Moderate (about 7 days) | Double first injection or first week total |
| Testosterone cypionate | Moderate-long (about 8 days) | Double first injection or first week total |
| Boldenone undecylenate | Very long (weeks) | Higher first week total, often 1.5–2x planned weekly dose |
| Testosterone undecanoate | Extremely long | Frontloading rarely practical |
Peak and trough management with frontloading
A larger initial dose creates a larger initial peak. For some users, that peak can mean more pronounced side effects such as water retention, mood changes, acne, or elevated oestrogen-related symptoms. Splitting the frontload into several smaller injections over the first week may smooth the peak while still accelerating the ramp-up.
Injection frequency matters more than many people realise. The same weekly total produces a smoother curve when divided into smaller, more frequent injections. This is especially relevant during a frontload, when the total amount entering the body in a short window is higher than usual.
Frontloading: Reality or Myth?
Evidence from user experience and pharmacokinetic theory
From a pharmacokinetic standpoint, frontloading follows established loading-dose principles for compounds with known half-lives. The model predicts that a higher initial dose will produce higher early blood levels. However, the practical evidence for non-medical steroid cycles remains limited.
User experience is harder to quantify. Some users report that cycles feel more productive earlier, but subjective feedback is influenced by expectation, training intensity, and other compounds in the stack. There are no large controlled studies comparing frontloaded and non-frontloaded steroid cycles in trained athletes, so the practical evidence remains informal.
Debate: early action vs peak blood hormone levels
One source of confusion is the difference between blood hormone levels and biological action. Frontloading can raise blood levels faster, but it does not make muscle tissue respond instantly. Receptor binding, protein synthesis, nitrogen retention, and recovery changes all take time to manifest.
Some critics argue that the early weeks of a cycle are valuable precisely because the body adapts gradually, and that raising levels quickly increases side effects without adding much real benefit. Others argue that if the goal is to spend as much time as possible near the intended exposure, frontloading is a logical way to use the cycle more efficiently.
Limitations and considerations (not magic, still ester-dependent)
Frontloading is not a way to bypass ester chemistry. A long ester still releases slowly, and there is a limit to how much can be introduced into the bloodstream at once. Extremely high opening doses can create uncomfortable peaks, injection-site issues, and management challenges without dramatically improving outcomes.
It also does not automatically reduce the total amount of drug used. In some plans, the same total milligrams are consumed; in others, the opening dose increases the total over a fixed cycle unless later doses are adjusted. Users who think frontloading lets them use less total drug are misunderstanding the concept.
Whether frontloading fits different cycle goals
Frontloading may be considered in cycles that are relatively short, centred on long esters, or structured around a clear performance window. It may also appeal to users who want to assess response and side effects sooner, although a higher early dose can make that assessment more difficult.
It may fit less well for beginners who are still learning how they respond to compounds, for cycles built mostly on short esters, or for users who prioritise stable mood and fewer side-effect spikes over a faster rise in blood levels. As with other cycle decisions, the balance depends on the individual’s goals, experience, risk tolerance, and medical circumstances.
This article is for informational purposes only and is not a medical recommendation, diagnosis, or treatment plan. Discuss any plans involving hormones or injectable compounds with a qualified healthcare provider before starting, especially if you have chronic conditions, take prescription medications, or are pregnant or planning pregnancy. Individual responses vary, and no specific result can be promised.